What Is the Anion Gap?
The anion gap is a calculated value used to evaluate acid-base balance and identify hidden causes of metabolic acidosis. It is not directly measured; instead, it is derived from standard serum electrolytes on a standard chemistry test. The most common version of the calculation uses serum sodium, serum chloride, and serum bicarbonate.
Clinicians use the anion gap to search for changes in unmeasured anions in the blood. These are ions that are present but not included in the routine electrolyte panel. When unmeasured acids accumulate, the gap often increases, signaling a form of high anion gap metabolic acidosis. That makes the anion gap a useful assessment tool for diagnosing metabolic derangement and narrowing the cause of an acid-base problem.
In simple terms, the calculation compares the positively charged sodium against the negative chloride and bicarbonate. A reduced bicarbonate level or a rise in other acidic substances can alter the balance. Because the formula depends on laboratory values from an electrolyte panel, interpretation should always consider the full serum chemistry picture, not one number alone.
The expected reference range can vary depending on the laboratory and the calculation method. Some labs also report an adjusted value if albumin is low, since albumin is a major unmeasured anion. This is why the anion gap is best viewed as a clinical tool for diagnostic interpretation, rather than a standalone diagnosis.
How Lactate Acidosis Affects the Anion Gap
Lactic acid buildup is a well-known cause of acid-base acidosis with a raised anion gap. It happens when the lactate builds up faster than the body can clear it, usually because oxygen transport or use is impaired, or because lactate production is greater. As lactate rises, it acts as one of the acid-forming molecules contributing to the acid load.
Why does the gap widen? The answer lies in buffering and electrical balance. When acids build up, bicarbonate is consumed as the body tries to buffer the excess hydrogen ions. At the same time, the accompanying anions from the acid, including lactate, remain in circulation. These extra anions are part of the pool of undetected anions, so the calculated anion gap increases.
This is why elevated lactate is commonly associated with raised anion gap metabolic acidosis. In practical terms, if a patient has a low bicarbonate on the metabolic panel and the anion gap is above the expected range, lactic acidosis is one major possibility. The presence of elevated lactate supports that interpretation, but the full clinical context still matters.
In many cases, lactic acidosis reflects poor oxygen delivery at the tissue level. Cellular hypoxia, reduced blood flow to tissues, and increased anaerobic metabolism all contribute NAGMA causes to the buildup of lactate. The result is a metabolic shift that can be seen in the blood gas and in routine laboratory values. The pattern often points toward a broader physiologic problem, not just a single abnormal number.
For that reason, an anion gap change is often a signal rather than the entire answer. The gap helps confirm that there is an acid burden from unmeasured acids, while the lactate level helps identify whether lactate is the main driver.
Could Lactic Acidosis Always Cause a High Anion Gap?
No, it does not. Although lactic acidosis often causes a high gap, it does not always do so. A patient may have lactate elevation with a normal anion gap under some conditions. That is one reason clinicians should not rely on the anion gap alone to rule in or rule out lactic acidosis.
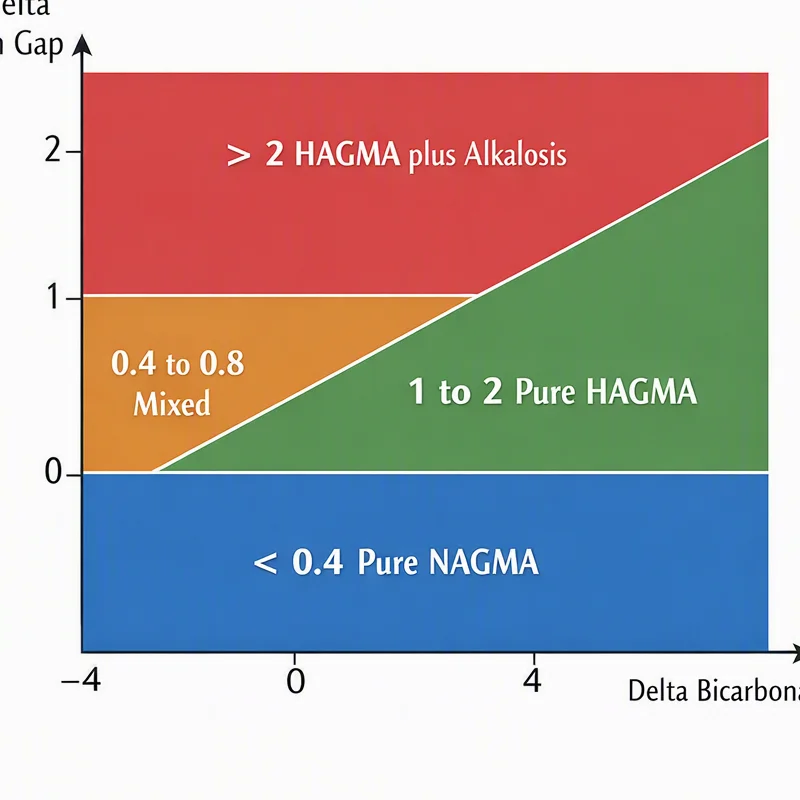
Another explanation is timing. In the early stages in the process, the chemistry may not yet fully reflect the acid load. Another reason is that the total change in measured ions may be dampened by other concurrent abnormalities. A patient with a mixed acid-base disorder may have overlapping processes that mask the expected pattern. For instance, metabolic acidosis may coexist with metabolic alkalosis, making the anion gap appear less marked than expected.
Albumin is another key factor. Since albumin is an important unmeasured anion, low albumin can make the anion gap appear falsely normal or only mildly elevated. This is why albumin correction is important. If albumin is reduced, the corrected anion gap may better reflect the true burden of unmeasured acids.
A patient can also have lactic acidosis and still show a normal anion gap if the bicarbonate and chloride changes offset the expected rise. That can happen in complex clinical states or when there is a mixed acid-base disorder. So while lactic acidosis is commonly associated with high anion gap metabolic acidosis, the absence of a high gap does not completely exclude it.
In short, the anion gap is a useful clue, but MUDPILES mnemonic examples it must be interpreted alongside the lactate level, albumin status, blood gas results, and the overall clinical assessment.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator streamlines the anion gap calculation by leveraging the numbers already present on an electrolyte panel. In most cases, you enter serum sodium, serum chloride, and serum bicarbonate. The calculator then estimates the gap and matches it with the expected reference range.
This matters because the calculation is easy to overlook during a busy metabolic panel review. The calculator helps improve clinical interpretation and reduces the chance of arithmetic errors. It can also help determine whether the pattern fits metabolic acidosis with increased unmeasured anions.
When using the tool, check the exact lab values and whether the calculator includes albumin correction. If albumin is low, the uncorrected gap may miss the problem. Correcting for albumin improves interpretation, especially when looking for occult high anion gap metabolic acidosis.
An easy approach is:
- Review the electrolyte panel for sodium, chloride, and bicarbonate. Determine the anion gap using the Anion Gap Calculator. Compare the result with the lab’s reference range. Confirm that albumin is low and apply albumin correction if needed. Use the result with other laboratory values for diagnostic interpretation.
A calculator is most useful when paired with the broader picture: the patient’s symptoms, vital signs, blood gas, lactate, and other serum chemistry findings. The numbers guide the reasoning, but they do not replace clinical assessment.
Frequent Causes of Elevated Anion Gap Apart From Lactic Acidosis
Although lactic acidosis is a common cause of elevated anion gap, it is not the only reason. A number of other conditions create organic acids or further increase unmeasured anions in the blood. A careful differential diagnosis is important when interpreting a high gap.
An important category is ketoacidosis. Examples include diabetic ketoacidosis, alcoholic ketoacidosis, and starvation-related ketoacidosis. In these settings, ketone bodies accumulate and produce an acid burden comparable to lactate-related acidosis. The result is often a form of high anion gap metabolic acidosis.
Renal failure is yet another important cause. When kidney function declines, the body cannot clear acid effectively, and retained acids contribute to a widening gap. This is part of a broader metabolic derangement that may also involve other electrolyte shifts and impaired buffering.
Toxins and toxic alcohols are also key considerations. Ingestions involving substances such as methanol can produce dangerous acid-base disturbances. These cases may present with severe metabolic acidosis and a substantially elevated gap, often requiring urgent intervention. Because toxic alcohols can be life-threatening, they should be considered whenever the clinical picture and laboratory values are concerning.
Further causes may include salicylates and certain inborn errors of metabolism, but the key point is that an elevated gap points to a category of problems, not just one diagnosis. That is why the pattern should be interpreted in context, especially when lactate is only mildly elevated or when another process is clearly present.
When Lactic Acidosis May Not Be the Only Problem
Commonly, lactic acidosis is only part of the picture. It may occur alongside other drivers of acidosis or coexist with conditions that worsen the overall acid-base balance. In patients with critical illness, this overlap is typical and can make the laboratory pattern more difficult to interpret.
Sepsis is a major example. In sepsis, infection can trigger inflammation, impaired circulation, and metabolic stress. The result may be elevated lactate, but also other abnormalities that drive acid-base changes. The combination of infection and poor oxygen delivery can worsen tissue perfusion and intensify lactate accumulation.
Hypoperfusion and shock are especially important because they directly decrease oxygen delivery to tissues. When cells cannot access enough oxygen, they shift toward anaerobic metabolism, increasing lactate production. In shock states, the anion gap may rise as part of a broader syndrome of circulatory failure and metabolic disturbance.
At the same time, a patient may have a mixed acid-base disorder. For example, vomiting, diuretic use, respiratory changes, or renal compensation can alter the expected response. This can make the anion gap harder to interpret. A patient may have both an elevated lactate and another acid-base process that partially offsets the expected laboratory changes.
Because of this complexity, the best approach is to integrate the anion gap with the clinical picture, the metabolic panel, the lactate level, and the blood gas. That combined approach helps identify the dominant etiology and avoids missing multiple overlapping problems.
A normal or borderline gap does not always mean lactate is unimportant, and a high gap does not automatically prove lactic acidosis. The full pattern matters.
FAQ
Does lactic acidosis elevate the anion gap?
Absolutely. Lactic acidosis often increases the anion gap because lactate is an unmeasured anion that builds up during metabolic acidosis. As bicarbonate gets used up during buffering, the gap often rises, leading to high anion gap metabolic acidosis. However, the exact result depends on the overall laboratory values and clinical context.
Will every patient with lactic acidosis show a high anion gap?
No. Some patients with lactic acidosis can have a normal anion gap, particularly when there is a mixed acid-base disorder, low albumin, or early disease before the chemistry fully changes. This is why the gap should be interpreted with the lactate level and other laboratory results.
How does the Anion Gap Calculator work?
An Anion Gap Calculator relies on an electrolyte panel, usually serum sodium, serum chloride, and serum bicarbonate. It calculates the anion gap calculation and checks the result against the usual reference range. Some tools also offer albumin correction to enhance interpretation.
What other causes can lead to a high anion gap besides lactic acidosis?
Common causes include ketoacidosis, renal failure, and toxic alcohols such as methanol. Additional toxins and organic acids can likewise elevate the gap. The goal of the anion gap is to help narrow the differential, not to identify a single diagnosis by itself.
When should albumin be taken into account when reading the anion gap?
Albumin should be considered any time it is low or may be low, because it is a key unmeasured anion. Low albumin can make the gap appear normal even when acids are present. Using albumin correction improves clinical interpretation, especially in people with significant illness, sepsis, or other causes of altered serum chemistry.